What Does the Anion Gap Mean?
The anion gap is a computed value used for assessing plasma and serum electrolytes in a routine electrolyte panel. It represents the gap between the major measured cations and anions, mainly sodium on one side and chloride plus bicarbonate on the other. Because routine lab testing does not measure every charged particle in blood chemistry, the anion gap helps estimate the amount of unmeasured anions and assists in evaluating acid-base balance.
This concept is rooted in electroneutrality, the principle that plasma must remain electrically balanced overall. The calculated anion difference is not a direct measurement of a single substance; instead, it is a helpful indicator in clinical interpretation and diagnostic evaluation. When the gap is abnormal, it can point to a metabolic disturbance even before the underlying cause is fully known.
The anion gap calculator is designed to make easier this process. By entering common lab values, you can estimate whether the result falls within the expected lab reference range and decide whether further testing or closer review is needed. In practice, the anion gap is often used as part of a broader electrolyte panel and overall assessment of serum chemistry.
How the Anion Gap Calculator Works
An anion gap calculator uses a straightforward formula based on the recorded concentrations of chloride and bicarbonate compared with sodium. The standard equation is:
Anion gap = Sodium − (Chloride anion gap in chronic kidney disease + Bicarbonate)This formula helps identify whether the body is retaining extra acids or reducing key buffering capacity. The calculation is quick, but the meaning depends on the full clinical context. A normal number does not always rule out illness, and an abnormal number does not automatically confirm one diagnosis.
The calculator is highly useful because it converts a set of routine lab values into a result that supports result interpretation. If the numbers are outside of the expected reference interval, clinicians may consider whether there are additional acids, changes in protein balance, or even a lab measurement issue. In other words, the calculator does more than offer a number; it supports risk stratification during evaluation of possible acid-base problems.
How to Determine Anion Gap Step-by-Step
To perform the calculation, use the values from a standard chemistry panel. Use serum sodium, serum chloride, and serum bicarbonate from the same sample whenever possible. Consistency matters because small differences in sampling or timing can affect the result.
Follow these steps:
- Locate the sodium value from the lab report. Combine the chloride and bicarbonate values together. Remove that sum from the sodium value.
For instance, if serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the anion gap is 140 − (104 + 24) = 12. That result may fall within a usual normal range, depending on the lab method and local reference interval.
Since this calculation uses routine serum chemistry, it is important to verify the numbers carefully. A small transcription mistake can alter the answer significantly. The calculator is a helpful tool, but accurate input is essential for reliable diagnostic evaluation.
Normal Anion Gap Range and Reference Limits
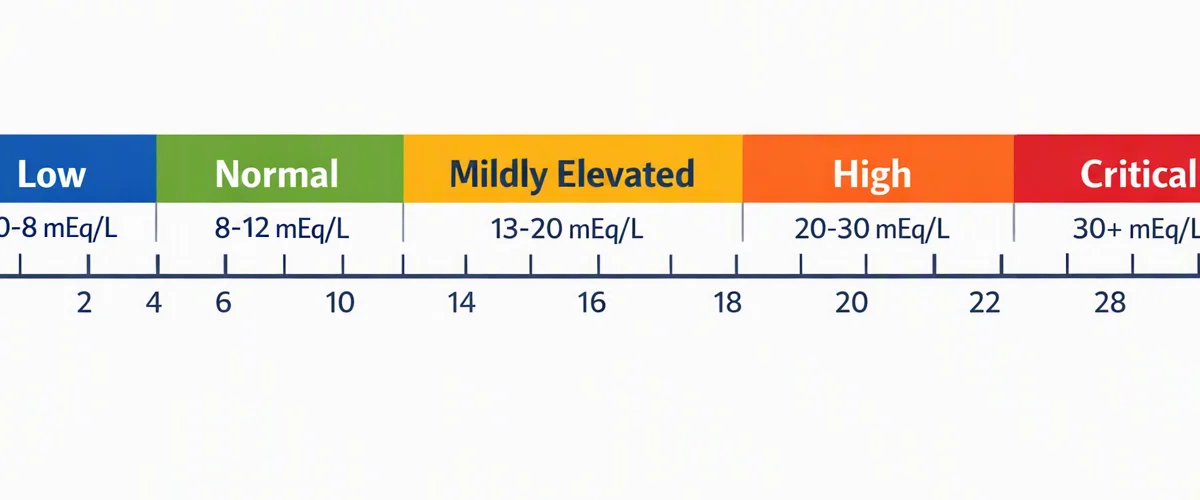
The usual range for anion gap differs by laboratory because different analyzers and methods yield slightly different results. That is why the reference range on the report should always be checked in place of relying on a fixed universal cutoff. In many settings, the reported test values fall into a narrow band, but the exact range depends on the assay and whether potassium is included in the calculation.
Albumin also affects the expected result because it is one of the most important unmeasured anions in plasma. When albumin is low, the anion gap may appear artificially normal or low even if clinically important acids are present. For that reason, understanding the local test reference range and considering albumin correction are both essential.
A result should always be interpreted in combination with symptoms and other chemistry findings. A single number cannot replace the broader picture of blood chemistry, especially when assessing possible acid-base abnormalities.
Elevated anion-gap Causes
A elevated anion gap often indicates additional unmeasured acids in the bloodstream and is commonly associated with acidic blood imbalance. The best-known form is high anion gap metabolic acidosis, which commonly suggests that acid production has risen, acid clearance has gone down, or the two.
Common causes include:
- Lactic acidosis, commonly related to tissue hypoperfusion, severe infection, or other systemic stress. Ketoacidosis, such as diabetic ketoacidosis or starvation ketosis, where ketone acids collect. Kidney failure, in which the kidneys cannot remove acids properly. Alcohol toxins, including substances that can produce acidic metabolites.
Other poisons may also be involved, and the pattern can help guide urgent clinical interpretation. A high value is not a diagnosis by itself; it is a signal to investigate the cause of the acid-base abnormality. In practice, the calculator supports early recognition of an abnormal pattern so clinicians can focus on confirmatory tests, evaluate symptoms, and assess severity.
Because many causes overlap, the anion gap should be interpreted alongside medical history, physical findings, and other lab data. The presence of vomiting, altered breathing, dehydration, or confusion can change the differential and point toward a specific metabolic disturbance.
Reduced Anion Gap Factors
A reduced anion gap is uncommon, but it can still be important. One of the most important causes is reduced albumin, since albumin is a major contributor to overall electrical balance. When albumin decreases, the measured gap may also fall, even if there is no major change in the underlying acid-base balance.
Other causes include myeloma, where abnormal proteins can change the charge balance in blood. elevated calcium may also be associated with a reduced value in some cases. Sometimes the issue is not a medical condition at all but laboratory error or a sample handling issue such as sample contamination or instrument variation.
Because a decreased reading may reflect either real pathology or testing error, it should not be ignored. If the result is unexpected, clinicians often repeat the test, review the full electrolyte profile, and consider whether the finding matches the patient’s symptoms and other blood chemistry values. This is where the calculator is valuable as a screening and interpretation aid, but not as a final answer.
How Albumin Affects the Anion Gap
Correction for albumin is important because albumin is a major negative-charge carrying protein in blood plasma and plays a role in overall ionic balance. Since albumin behaves as an occult anion, low albumin can reduce the observed anion gap. In patients with significant hypoalbuminemia, the uncorrected number may fall short of the true degree of acid accumulation.
The albumin-corrected anion gap helps compensate for this by revising the measured value based on the serum albumin concentration. Various institutions may use slightly different correction formula approaches, but the overall goal is the same: to estimate what the gap would be if albumin were normal. This improves interpretation when evaluating possible unmeasured anions in acid-base problems.
Albumin correction is most useful when clinical suspicion is high but the measured gap looks normal. In that setting, the correction can reveal hidden acidic imbalance and raise the quality of diagnostic review. It also helps avoid false reassurance when low albumin is masking the true picture.
Healthcare Analysis of Results
The anion gap is most useful when interpreted as part of a comprehensive acid-base disorder review. A number deviating from the expected range may indicate an electrolyte imbalance, but the meaning depends on the patient’s complaints, vital signs, and other labs. For example, a high gap with low bicarbonate clearly supports an acid load problem, while a low or normal gap does not exclude disease if albumin is reduced.
An arterial blood gas can help establish whether the patient truly has acidemia or alkalemia and whether respiratory compensation is sufficient. Pairing the anion gap with blood gas data strengthens clinical interpretation and supports more accurate symptom assessment. This is especially helpful when the presentation is complex.
In practice, the anion gap is one piece of the larger puzzle. It can help narrow the differential, but final interpretation requires the full clinical context, including medications, kidney function, perfusion status, nutritional state, and possible exposures. That broader view helps differentiate a transient metabolic disturbance from a more serious condition.
Common Applications for the Anion Gap Calculator
The anion gap calculator is used commonly in emergency medicine and the ICU, where rapid decision-making matters. In those settings, clinicians often need a quick way to spot patients with possible acid accumulation, especially when blood gas or chemistry results are being reviewed in real time.
It also serves as a useful screening and diagnostic tool in outpatient and inpatient care. When a routine electrolyte panel shows an unexpected change, the calculator helps decide whether the pattern suggests AG formula Na - (Cl + HCO3) a more serious acid-base issue or a less urgent explanation. This can direct next steps in evaluation and help prioritize confirmatory workup.
Because it is easy to apply, the calculator enables rapid risk stratification. That does not replace formal medical evaluation, but it helps clinicians determine which patients may need additional labs, closer observation, or urgent treatment.
Limitations and When to Confirm with Lab Testing
Although helpful, the calculator has limitations. The result depends on correct inputs and on the accuracy of the underlying lab measurement. Even minor measurement error can alter the final number, particularly when the gap is near the cutoff between normal and abnormal.
A venous blood test is often the source of the electrolyte values used in calculation, and repeat sampling may be needed if the result fails to match the clinical picture. Repeat testing is especially important when the finding is unexpected or when a treatment decision depends on it. The overall precision of the result improves when the sample is handled properly and analyzed promptly.
Additional confirmation is also important when albumin is very low, when there is concern for toxic ingestion, or when the patient has a complex metabolic disturbance. In those cases, the calculator should be considered a component of broader clinical interpretation, not the final word.
FAQ
What is a normal anion gap?
A normal anion gap is the result expected within a laboratory’s reference range, but the exact cutoff depends on the method used and the local lab reference range. Because analyzers differ, it is best to compare the result with the specific report rather than a universal number. Albumin level can also shift the expected value.
How do I calculate the anion gap from sodium, chloride, and bicarbonate?
Apply the standard formula: sodium minus the sum of chloride and bicarbonate. In other words, sodium − ( chloride + bicarbonate). This is the core calculation used by any anion gap calculator. Make sure the values come from the same blood sample to improve accuracy.
Why should I correct the anion gap for albumin?
Albumin correction matters because albumin is a primary unmeasured anion and changes overall charge balance. With low albumin, the measured gap may appear falsely normal or low. The corrected anion gap offers a more accurate estimate of the true acid base picture.
What leads to a high anion gap?
A high anion gap is often caused by metabolic acidemia from extra acids in the blood. Common causes include lactic acidosis, ketone buildup, kidney failure, and exposure to toxic alcohols. Other toxins may also play a role, so the result should be read with the full clinical context.
Can a low anion gap be a sign of a medical problem?
Absolutely. A low anion gap can reflect hypoalbuminemia, myeloma, or high calcium, and it can also result from testing error. If the value is out of range, it should be reviewed thoroughly and often confirmed with repeat testing. The finding is not necessarily dangerous, but it should not be dismissed without further evaluation.