What the Anion Gap Indicates
The anion gap is a useful way to determine the difference between routinely measured electrolytes in the blood and the unseen charged particles that help maintain acid-base balance. Clinically, it is most often used to support evaluation of metabolic acidosis and other acid-base disorders.
An anion gap calculator uses typical laboratory values such as sodium, chloride, and bicarbonate to help identify whether there are additional unmeasured anions in the plasma. In everyday practice, this is a helpful part of clinical interpretation because it can point toward a certain metabolic derangement even before the full picture is known.
The core idea is simple: sodium represents most of the measured positive charge, while chloride and bicarbonate represent primary measured negative charges. The gap reflects the relationship between these laboratory values and the unseen ions that are not directly reported on a standard electrolyte panel.
Although the number itself is only one piece of the puzzle, it is a valuable screening tool for identifying an abnormal acid-base state and guiding a more focused diagnostic algorithm. In settings such as critical care, the anion gap can help identify whether a patient likely has an acid-base disturbance that needs prompt workup.
How to Operate an Anion Gap Calculator
To use an anion gap calculator, start with a serum chemistry panel and enter the input values for sodium, chloride, and bicarbonate. Several calculators also permit entry of serum albumin, which is important when you want an albumin-corrected anion gap.
The calculator calculates the anion gap formula and produces a value that can be compared with the expected reference range. A result above the expected range may suggest excess acids or other unmeasured anions, while a normal value does not fully exclude an acid-base disorder.
For clinical use, the process should be methodical:
- Confirm the basic electrolyte values on the serum chemistry panel. See whether serum albumin is available. Enter the input values carefully to avoid transcription mistakes. Examine the calculated anion gap in the context of the patient’s symptoms and other laboratory values. Assess whether an albumin correction is needed before interpreting the result.
The calculator is best used as a decision-support aid, not as a standalone diagnosis. A single number does not replace bedside assessment, medication review, or more advanced acid-base analysis. Instead, it helps clinicians identify patterns that warrant a closer look.
Anion Gap Formula and Calculation Methods
The classic anion gap formula is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Several laboratories and references include potassium in the formula:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Both versions are used in clinical practice, but the sodium-only version is more standard because potassium contributes relatively little to the total. Still, it matters to know which method your calculator uses so you can match the result with the correct reference range.
The corrected anion gap is particularly important when serum albumin is low. Because albumin is a major unmeasured anion, low levels can make the uncorrected gap appear falsely normal. In that setting, albumin correction helps reveal hidden acid accumulation that might otherwise be missed.
For practical use, the calculator should readily show which method is being applied. That prevents confusion when the result is reviewed alongside other electrolytes and supports more reliable diagnostic support in real-time care.
Expected Anion Gap Range and Interpretation
The expected reference range for the result depends on the assay method, testing platform, and whether potassium is included. As a result, there is not a single standard normal number. Rather, clinicians should interpret the result using the lab-specific range reported with the patient’s laboratory values.
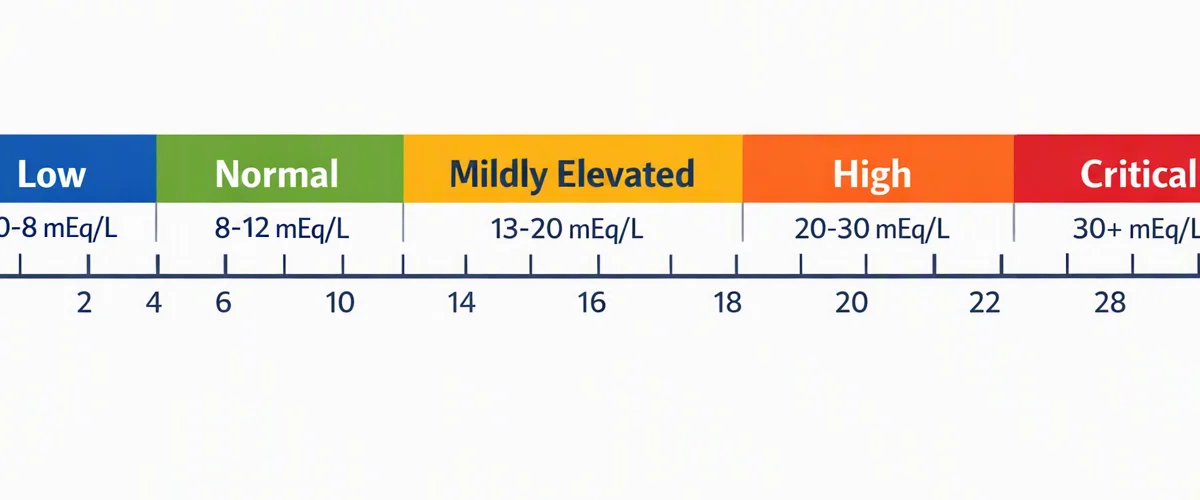
A normal anion gap often suggests that the balance between measured cations and anions is appropriately balanced, but it does not rule out disease. A patient may still have normal anion gap metabolic acidosis, especially if there is a compensatory rise in chloride.
A high anion gap points toward accumulation of acids or other unmeasured substances. That finding is especially important when evaluating possible metabolic acidosis. However, the degree of elevation may be blunted by hypoalbuminemia or affected by lab variation.
Clinical review should anion gap in chronic kidney disease always consider the full clinical picture:
- Is there acidemia on blood gas testing? Are there signs of shock, hypoperfusion, or toxin exposure? Do the electrolytes show concurrent hyperchloremia? Is the bicarbonate reduced in a way that matches the expected pattern?
These questions turn a raw value into meaningful clinical interpretation.
Reasons of High Anion Gap Metabolic Acidosis
High anion gap metabolic acidosis occurs when acids collect more quickly than the body can clear them or neutralize them. This results in a rise in unmeasured acid anions and a decrease in serum bicarbonate.
Typical causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, reduced oxygen delivery or mitochondrial dysfunction leads to lactate accumulation. In ketoacidosis, ketone bodies accumulate in states such as diabetic decompensation, starvation, or alcohol-related metabolic stress. In renal failure, the kidneys cannot excrete acid effectively, so retained organic acids widen the anion gap.
Other causes can include toxic ingestions, but the most clinically common scenarios are those above. The practical value of the calculator is that it signals clinicians to a pattern that matches a metabolic derangement even before all confirmatory testing is complete.
In real-world assessment, a high result should prompt a search for the underlying driver rather than a focus on the number alone. The next step is to find whether the elevation is due to hypoperfusion, insulin deficiency, kidney dysfunction, or another process affecting acid-base balance.
Reasons for normal anion gap metabolic acidosis
Normal anion gap metabolic acidosis is also known as hyperchloremic acidosis. In this condition, bicarbonate is lost or consumed, and chloride rises to keep electrical balance. As a result, there is a lowered serum bicarbonate with a relatively unchanged gap.
A well-known cause is diarrhea, which results in direct digestive bicarbonate loss. Another key cause is renal tubular acidosis, where the kidneys do not adequately acidify urine or reabsorb bicarbonate, resulting in continued acid-base disturbance.
Because chloride rises as bicarbonate falls, the measured chloride may appear disproportionately high. That pattern helps separate this disorder from a raised-gap process. Still, mixed disorders can occur, so the calculator should be viewed as one component of a broader diagnostic algorithm.
In practice, recognizing hyperchloremia alongside low bicarbonate can help narrow the cause of metabolic acidosis and prevent overlooking a normal-gap pattern that needs a different workup than lactic acidosis or ketoacidosis.
Why Albumin Changes the Anion Gap
Serum albumin is a major factor to the body’s hidden negative anion load. Because of that, hypoalbuminemia can reduce the apparent anion gap even when acid build-up is present. This is why albumin-corrected anion gap values are so useful in clinical interpretation.
The association is grounded in protein charge: albumin carries a negative charge at physiologic pH, so when albumin decreases, the measured gap may also fall. In patients with critical illness, low albumin is common, which makes uncorrected results less reliable.
Albumin correction helps clinicians avoid a false sense of reassurance. A patient with sepsis, shock, or organ failure may have a “normal” raw value but still carry a clinically significant high anion gap metabolic acidosis once the correction is performed.
For this reason, many clinicians prefer using a calculator that includes plasma albumin or serum albumin as an input. That approach improves the usefulness of the anion gap calculation as a practical screening tool and promotes better recognition of unmeasured acid excess.
Common Clinical Issues and Typical Computation Errors
Several pitfalls can make an otherwise useful result inaccurate. One common issue is laboratory error, including contaminated specimens, delayed processing, or an analyzer problem. If the result does not fit the patient’s condition, rechecking is important.
A common error is failing to recognize mixed acid-base disorders. A patient may have both an elevated gap and a concurrent metabolic process that masks the expected bicarbonate change. This is especially relevant in sicker inpatients.
Potassium omission is another source of confusion. If a calculator includes potassium and the clinician expects a sodium-only formula, the numbers will not match. Always know which anion gap formula is being used.
Unit mismatch can also distort the calculation. Input values must be in the correct units, and the calculator should not be fed values from different reporting systems without confirmation. Even small entry errors can create an incorrect impression of a major electrolyte disturbance.
Good clinical practice is to treat the calculator as one part of an acid-base analysis, not the final answer. If the result is unexpected, recheck the raw electrolytes, review the chart, and compare the trend with prior laboratory values.
When to Recheck Labs or Request Further Testing
Further testing is appropriate when the anion gap does not match the clinical picture, when the patient appears unstable, or when the result suggests a serious metabolic derangement. A repeat panel can help confirm whether the abnormality is persistent or due to transient variation.
An arterial blood gas Have a peek at this website is useful when you need a broader assessment of acid-base status, including pH and respiratory compensation. This is especially helpful if the bicarbonate value and clinical findings do not align.
Additional focused tests may include serum lactate when lactic acidosis is thought possible, or ketones when ketoacidosis is a concern. When the history suggests ingestion of a toxin or an unusual osmotically active compound, an osmolar gap may offer helpful clues.
Checking again is also warranted if there is concern about laboratory error, sample handling issues, or a changing clinical condition such as evolving renal failure. The goal is to use the calculator as a starting point for focused workup, not as an answer.
If interpreted correctly, the tool can support timely decisions, aid recognition of metabolic acidosis, and support a more structured response to acid-base abnormalities.
FAQ About the Anion Gap
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the difference between measured cations and anions on a serum chemistry panel. In practice, it helps assess acid-base balance, detect possible unmeasured anions, and support evaluation of metabolic acidosis. It is especially useful as a screening tool and part of broader clinical interpretation.
What is a normal anion gap range?
The normal range depends on the laboratory method and whether the calculation includes potassium. Because of lab variation, the best comparison is the facility-specific reference range that accompanies the patient’s results. A normal number does not exclude all acid-base disorders, especially normal anion gap metabolic acidosis.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate. Some methods include potassium. The key is to use the same method as the calculator or laboratory report and check the units before interpreting the result.
Why do you correct the anion gap for albumin?
You correct to account for albumin because serum albumin is a key unmeasured anion. With hypoalbuminemia, the raw gap may seem falsely normal. An albumin-corrected anion gap helps detect hidden acid accumulation and strengthens the detection of high anion gap metabolic acidosis, especially in critical illness.
What situations cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. Other causes exist, but these are among the most common and important in practice. When the gap is high, clinicians should search for the underlying source of acid production or impaired acid clearance and pursue additional testing if needed.