How the Anion Gap Measures
The anion gap is a computed value used in acid-base status assessment to help spot an electrolyte imbalance or a concealed acid-base disorder. It compares the major measured cations and anions in the blood and gives clinicians a clue about the presence of unmeasured anions that may be contributing to a metabolic disturbance.
In standard practice, the anion gap is derived from a serum chemistry or electrolyte panel, especially from serum sodium, serum chloride, and serum bicarbonate. These values reflect the balance of charged particles in the bloodstream and are part of the body’s buffer system. When the balance shifts, the anion gap can help refine the differential diagnosis.
Clinically, the anion gap is a helpful biochemical marker during clinical assessment and patient evaluation. It does not diagnose a condition by itself, but it can signal that blood test results need closer review. An elevated gap often points toward high anion gap metabolic acidosis, while a normal result may still be informative depending on the broader picture.
How an Anion Gap Calculator Works
An anion gap calculator is a simple diagnostic tool that executes the anion gap calculation from routine lab values. Most calculators use the anion gap formula:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some versions also include potassium, but many modern calculations omit it because the contribution of potassium is limited in typical routine settings. In those cases, the formula becomes simpler and more convenient to apply from a standard blood chemistry result.
The calculator depends on a complete blood chemistry panel or electrolyte panel. A clinician or patient inputs the measured values for sodium, chloride, and bicarbonate, and the calculator provides the anion gap. The result can then be compared with the expected reference interval or reference range used by the laboratory.
This process is simple, but interpretation requires context. A single number does not replace laboratory interpretation or clinical judgment. The calculator is particularly valuable when paired with the rest of the serum chemistry, the patient’s symptoms, and other diagnostic data.
Typical Anion Gap compared with Increased Anion Gap
A normal anion gap often indicates that if acidosis is present, it may be due to depletion of bicarbonate rather than increase of unmeasured acids. By contrast, a high anion gap implies that additional acids are present in the blood, commonly leading to metabolic acidosis.
Because the usual range can vary between laboratories, the exact cutoff should be interpreted using the lab’s own reference interval. This is especially important when evaluating acid-base status in hospitalized patients or in critical care settings, where small changes can matter.
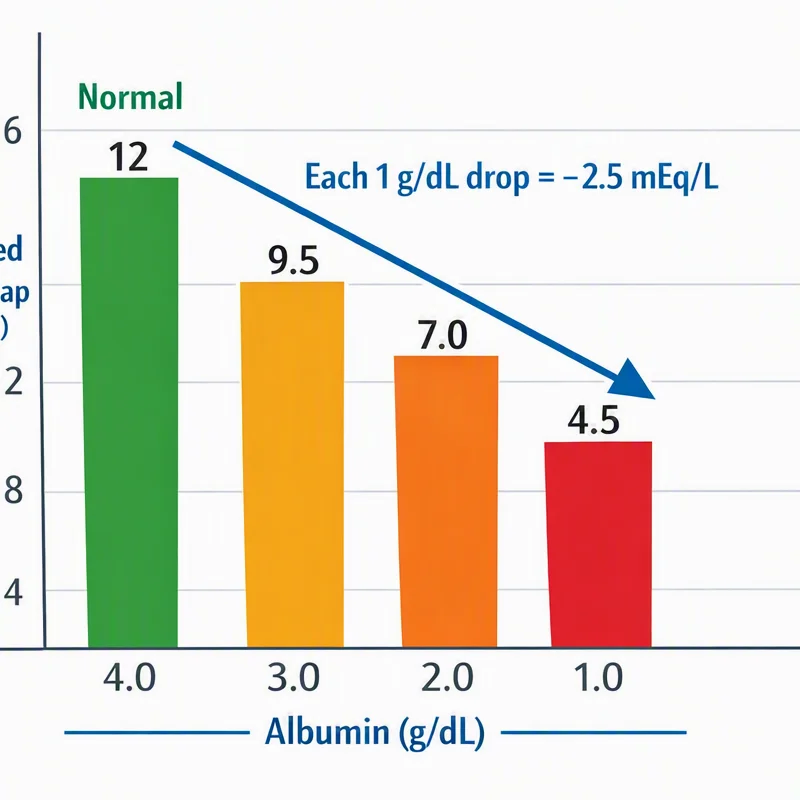
Albumin plays a major role in the interpretation of the anion gap because it is a negatively charged protein. When albumin is low, the measured anion gap may appear falsely normal or only mildly elevated. That is why a normal reading does not always exclude an acid-base disorder.
In practical terms, an elevated anion gap often indicates increased acids, while a normal anion gap may reflect bicarbonate loss, chloride retention, or a mixed disturbance. Understanding the pattern helps clinicians evaluate the result in relation to the patient’s overall clinical assessment.
Frequent Causes of High Anion Gap Metabolic Acidosis
Elevated anion gap metabolic acidosis arises when acids collect more quickly than the body can counteract or clear them. Multiple common causes should be kept in mind during differential diagnosis.
Lactic acidosis occurs when lactate accumulates, often due to inadequate oxygen delivery to tissues, sepsis, shock, seizures, or serious illness. It is a major cause of elevated anion gap in emergency and inpatient care settings.
Ketotic acidosis is a further classic cause. It can occur in diabetic ketoacidosis, starvation, or alcohol-related ketosis. In this setting, ketone bodies act as unmeasured anions and increase the gap.
Kidney failure can also raise the anion gap because impaired kidney function reduces acid excretion and allows organic acids to accumulate. Reviewing kidney function alongside electrolyte values is useful for a complete evaluation.
Alcohol-related toxins, such as methanol or ethylene glycol, are important to consider when the clinical picture suggests poisoning. These substances generate acidic metabolites and can produce a dangerous metabolic disturbance. They are a time-sensitive diagnosis and often require urgent treatment.
Other contributors may include advanced liver disease, certain medications, or severe tissue injury. The exact cause depends on the pattern of symptoms, the serum chemistry profile, and the broader medical context.
How to Understand Results in Clinical Context
The value from an anion gap calculator is especially useful when considered alongside the full clinical picture. A lone result cannot define the cause of illness, but it can guide medical decision-making and assist in deciding whether further testing is needed.
If the patient has signs of metabolic acidosis, an elevated gap may indicate that acid is accumulating. An arterial blood gas can then help confirm the acid-base pattern and show whether there is respiratory compensation. For example, a low pH with low osmolar gap and anion gap relationship bicarbonate and an elevated gap points to a primary metabolic process rather than a purely respiratory one.
The delta gap is a further important concept. It compares the rise in anion gap with the fall in bicarbonate and helps identify mixed disorders. This can reveal whether a patient has both a high-gap acidosis and another process, such as metabolic alkalosis or a normal-gap acidosis.
In clinical practice, the goal is not simply to describe a result as normal or abnormal. It is to use the result as part of laboratory interpretation that leads to a safer, more accurate diagnosis. That is why the anion gap is best viewed as one piece of a larger acid-base evaluation.
Correction of the Anion Gap for Low Albumin
Albumin correction is crucial when assessing the anion gap in patients with hypoalbuminemia. Since albumin is a primary unmeasured anion, a low level lowers the measured gap and can obscure an underlying disorder.
When albumin is reduced, clinicians often estimate a adjusted anion gap. This adjustment serves to restore the result closer to what would be expected at a normal albumin level. Without this step, the value may remain within the apparent reference range even when clinically important acids are present.
A common approach is to increase the measured anion gap by a set amount for each drop in albumin below normal. Different institutions may use slightly different formulas, so the exact method should follow local practice. The important point is that low albumin can lead to underestimation of the true acid burden.
This is especially pertinent in hospitalized patients, those with chronic illness, and patients undergoing critical care. In these settings, hypoalbuminemia is common and can alter both the interpretation and the urgency of further workup.
Step-by-Step Sample Calculations
Below is a sample computation using typical laboratory numbers. This illustrative calculation shows how the formula for the anion gap is implemented in everyday use.
Example 1: Standard calculation
Serum sodium = 140 mEq/L
Serum chloride = 102 mEq/L Serum bicarbonate = 24 mEq/LApplying the anion gap equation:
140 − (102 + 24) = 14
The anion gap is 14. If this is normal depends on the laboratory’s reference interval and whether potassium is included in the formula. If the result is near the upper end of the lab’s range, it may still be clinically acceptable, but the full context matters.
Example 2: Elevated anion gap
Serum sodium = 138 mEq/L
Serum chloride = 100 mEq/L Serum bicarbonate = 14 mEq/L138 − (100 + 14) = 24
That result is clearly elevated in many settings and may suggest high anion gap metabolic acidosis. Causes such as lactate-related acidosis, ketone-related acidosis, renal insufficiency, or toxic alcohols should be considered.
Example three: Albumin correction
Suppose the measured anion gap is 10 and albumin is low. anion gap in chronic kidney disease After adjustment for albumin, the corrected anion gap may rise into a higher range, revealing an abnormality that the uncorrected value missed. This is a common reason why albumin should always be reviewed when interpreting an electrolyte panel.
This set of examples show why the calculator is a beginning step, not the final answer. The number must be connected to symptoms, physical findings, and other testing.
Limitations and When to Get Medical Review
While a carefully built calculator has boundaries. A incorrectly abnormal result can occur because of laboratory error, collection problems, or transcription mistakes. That is why unexpected results should be rechecked before making major decisions.
The anion gap is only one part of acid-base analysis. It does not replace an arterial blood gas, a full electrolyte panel, or assessment of kidney function, glucose, lactate, and ketones when needed. It also does not identify the reason of an abnormal result on its own.
As interpretation affects healthcare decision-making, urgent symptoms should never be ignored. If a patient has severe weakness, confusion, rapid breathing, chest pain, dehydration, or altered mental status, prompt evaluation may be needed. In some cases, prompt care or emergency assessment is appropriate.
For anyone using an anion gap calculator as part of self-review or clinical screening, the best approach is to treat the result as a guide. If the number is unexpected, significantly high, or paired with concerning symptoms, professional review is important.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the anion gap from blood test values and help assess acid-base status. It is commonly used to screen for acid buildup, identify possible unmeasured acids, and support laboratory interpretation of an electrolyte panel.
What is a normal anion gap range?
The expected anion gap depends on the laboratory’s reference interval and whether potassium is included in the formula. In general, the result should be interpreted using the lab’s own reference interval rather than a single universal cutoff.
How do you calculate the anion gap from lab values?
Use the gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = serum sodium − (serum chloride + serum bicarbonate). Some versions include potassium, but many calculators omit it.
Why does low albumin levels affect the anion gap?
Albumin is a negatively charged protein and a important unmeasured anion. When albumin is low, the measured anion gap may look lower than it truly is. That is why albumin correction is important and why a corrected anion gap may be more accurate in patients with hypoalbuminemia.
What conditions can cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Additional causes may also be present, so the result should always be interpreted with the full clinical picture and, when appropriate, an arterial blood gas and other blood test results.