Understanding an Anion Gap?
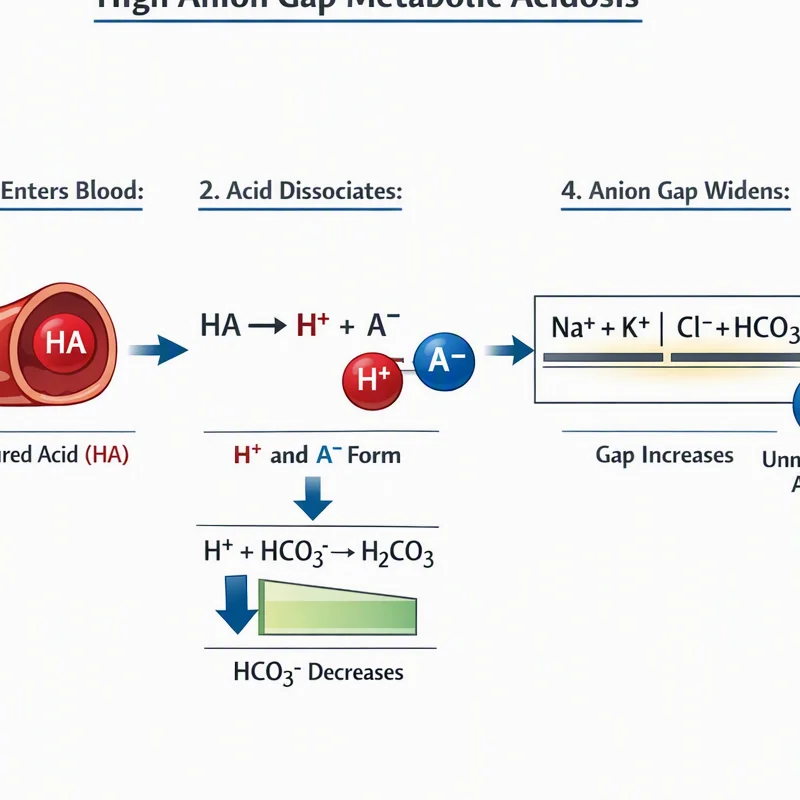
The anion gap is a derived value that helps to help evaluate acid-base balance and detect changes in a patient’s electrolytes. It compares the recorded cations and anions in a standard electrolyte panel, usually using serum sodium, serum chloride, and serum bicarbonate. As not every ion is directly assessed on routine serum chemistry testing, the anion gap acts as a useful helpful guide when interpreting a lab result.
In everyday use, the anion gap helps clinicians work through an acid-base disorder by showing whether there are unmeasured anions contributing to metabolic acidosis. A higher-than-expected value can point toward conditions with excess acids, while a normal value can suggest that bicarbonate has been lost and replaced by chloride. That distinction is particularly important when evaluating normal anion gap acidosis, also called non-anion gap metabolic acidosis or hyperchloremic metabolic acidosis.
The concept is basic, but the interpretation can be nuanced. Because sodium is a major measured cation and chloride and bicarbonate are major measured anions, the balance among them reflects the body’s internal chemistry. When serum chloride rises as bicarbonate falls, the anion gap may remain unchanged even though acidosis is present. That is why the anion gap is not just a number; it is part of a broader clinical assessment of a patient’s metabolic state.
How an Anion Gap Calculator Works
An anion gap calculator simplifies the calculation formula and lowers the chance of math errors. In its simplest form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This calculation uses standard laboratory values from an electrolyte panel. Some calculators may also include an albumin correction, because serum albumin is a major unmeasured anion and can shift the expected value. When albumin is low, the raw anion gap may look lower than it truly is, which can mask clinically important findings.
The calculator is most helpful when a clinician wants a rapid interpretation guide for a patient with suspected acidosis. It gives a quick estimate of whether the result falls within the expected reference interval or points to a deviation that needs further evaluation. A normal lab result does not always mean there is no problem; it may simply mean that the pattern is consistent with bicarbonate loss rather than added acids.
Many calculators also help identify a corrected anion gap by adjusting for hypoalbuminemia. That correction can be important in ill patients, where low albumin is common and may change the apparent picture. In other words, the calculator is a useful shortcut, but its output still requires thoughtful clinical interpretation in light of the full clinical context.
Normal Anion Gap Acidosis Overview
Normal anion gap acidosis is a type of acid-base imbalance in which the measured anion gap remains within the usual range despite a drop in bicarbonate. It is also called non-anion gap metabolic acidosis and hyperchloremic acidosis because chloride often rises to balance the lost bicarbonate. This keeps the anion gap from increasing even though the body’s acid-base balance has shifted toward acidity.
This pattern is distinct from high anion gap acidosis, where unmeasured acids collect. In normal anion gap acidosis, the key issue is usually bicarbonate loss or impaired renal acid handling rather than the production of new acids. The result is often described as a slight acidosis, but the severity depends on the underlying cause and the patient’s overall status.
Recognizing this pattern is useful because it narrows the differential diagnosis. A calculator can reveal that the anion gap is not elevated, but that finding should draw focus to chloride, bicarbonate, and the likely source of bicarbonate loss. In that sense, the anion gap calculator is a first step for evaluation, not the final answer.
Typical Causes of Regular Anion Gap Acidosis
Multiple conditions can lead to normal anion gap acidosis. A common cause is diarrhea, which results in gastrointestinal bicarbonate loss. When bicarbonate is lost from the gut, the body may hold onto chloride to preserve electrical neutrality, producing a high chloride pattern and a normal anion gap.
Another important cause is renal tubular acidosis, a group of disorders in which the kidneys have problems with kidney acid handling. In these conditions, the kidneys cannot excrete acid properly or fail to reclaim bicarbonate efficiently. The result can be a ongoing non-anion gap metabolic acidosis even when kidney function is otherwise not severely impaired.
Chloride-rich intravenous fluids can also be a factor. High amounts of chloride-rich solutions may dilute bicarbonate and increase serum chloride, leading to hyperchloremic metabolic acidosis. This is especially relevant when reviewing recent treatments, because the acid-base pattern may stem from therapy rather than a primary disease process.
Additional causes may include certain medications, fistulas, or renal disorders, but the most common practical categories are diarrhea, renal tubular acidosis, and chloride load. When the underlying cause is not apparent, the anion gap calculator can help narrow the workup on these pathways.
How to Read the Result
Interpreting the result begins with checking https://anion-gap-chart724.iamarrows.com/anion-gap-calculator-for-medical-use-and-assessment the serum electrolytes collectively, not in isolation. A low bicarbonate level plus a normal anion gap and elevated chloride often supports hyperchloremic metabolic acidosis. The next question is whether the pattern fits loss from the digestive tract, renal loss, or another source of bicarbonate loss.
Potassium is also important. Some forms of renal tubular acidosis are characterized by low potassium, while others may present with high potassium. That detail can help narrow the differential diagnosis and suggest which kidney acid handling defect is most likely.
The clinical context matters just as much as the numbers. A lab pattern consistent with metabolic acidosis may be found in a patient with diarrhea, recent fluid administration, or kidney disease. The calculator should therefore be used within a broader assessment that includes symptoms, medications, volume status, and recent treatments.
In practice, the best approach is to combine the calculator output with a careful clinical interpretation of the serum bicarbonate level, chloride level, potassium level, and the patient’s overall presentation. This helps determine whether the result reflects a transient change or a more significant acid-base disorder.
When to Revise the Anion Gap for Albumin
Albumin is one of the primary unmeasured anions in plasma, so low serum albumin can lower the observed anion gap. This means that a patient with hypoalbuminemia may have a seemingly normal or low anion gap even when a separate process is present. In those cases, using a corrected anion gap offers a more accurate picture.
Albumin correction is especially valuable when the clinical picture suggests more than simple bicarbonate loss. If the uncorrected value looks normal but the patient appears significantly ill, the correction may reveal a hidden disturbance. This is a matter of protein binding and ion balance, not just arithmetic.
Many anion gap calculators include albumin adjustment because it improves interpretation in patients with low protein levels. The key point is that the raw number can be deceptive when albumin is low. If a clinician ignores this, a mixed acid-base disorder may be missed.
As a rule, the lower the albumin, the more thorough the interpretation should be. Albumin correction does not substitute for clinical judgment, but it can improve the accuracy of the anion gap as a screening tool and help uncover an otherwise obscured acid-base disorder.
Stepwise Worked Calculation
This is a stepwise example using standard lab values:
Serum sodium: 140 mEq/L
Chloride: 112 mEq/L Serum bicarbonate: 20 mEq/LWith the calculation formula:
Anion gap = 140 - (112 + 20)
This equals 140 - 132 = 8 mEq/L.
If the lab’s reference range for the anion gap is roughly 8 to 12 mEq/L, this result is within the expected range. Still the low bicarbonate continues to indicate metabolic acidosis. Since the anion gap is normal, the pattern suggests non-anion gap metabolic acidosis, often related to diarrhea, renal tubular acidosis, or chloride load.
When the patient’s albumin is low, say due to hypoalbuminemia, the adjusted anion gap may be higher than 8. This is why the calculator should be viewed as part of the diagnostic workflow, not a standalone verdict. A normal raw value can still coexist with another acid-base issue if albumin is reduced or if there is a mixed disorder.
This example shows how a calculator supports the overall evaluation. It helps confirm that the pattern is consistent with normal anion gap acidosis and directs attention toward the cause of bicarbonate loss rather than excess unmeasured acids.
When to Order Additional Testing
Further evaluation is needed when the cause is unclear, the patient is symptomatic, or the result does not fit the rest of the clinical picture. A blood gas analysis can confirm the degree of acidemia and help distinguish respiratory from metabolic contributions. It is especially useful if the serum bicarbonate is low but the overall picture is uncertain.
A urine anion gap may be ordered when renal tubular acidosis is suspected. This may help distinguish kidney acid-handling problems from gastrointestinal bicarbonate loss by estimating whether the kidneys are appropriately excreting ammonium. In the setting of persistent non-anion gap metabolic acidosis, it can be a valuable next step.
Lactate testing may be useful if there is concern for a mixed disorder or if the clinical situation could involve poor tissue perfusion or another high anion gap process. Even if the anion gap calculator suggests a normal result, lactate can help eliminate additional contributors.
Kidney function tests are also helpful, especially when renal tubular acidosis, chronic kidney disease, or medication effects are part of the differential diagnosis. Together with blood gas analysis and urine studies, they help finish the evaluation and clarify the underlying cause.
Frequently Asked Questions
What is the normal anion gap range?
The anion gap normal range depends on the laboratory and whether potassium is included in the calculation. Many reference intervals fall around 8 to 12 mEq/L, but the exact range can change by method and analyzer. Always interpret the value using the lab’s own reference interval.
How do you calculate the anion gap with sodium, chloride, and bicarbonate?
Use the calculation formula: serum sodium minus the sum of serum chloride and serum bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). An anion gap calculator automates this process and helps minimize errors.
Why do you correct the anion gap for albumin?
You correct for albumin because low serum albumin can lower the measured gap and hide a clinically important disturbance. With hypoalbuminemia, the corrected anion gap gives a more precise reflection of the true acid-base state.
What causes normal anion gap acidosis?
Common metabolic acidosis causes with a normal gap include diarrhea, renal tubular acidosis, gastrointestinal bicarbonate loss, and exposure to chloride-rich intravenous fluids. These conditions usually reduce bicarbonate while elevating chloride, producing hyperchloremic metabolic acidosis.
When should a urine anion gap be ordered?
A urine anion gap is frequently ordered when the reason of normal anion gap acidosis is unknown and renal tubular acidosis is being suspected. It can aid differentiate kidney acid-handling abnormalities from gastrointestinal bicarbonate loss and is most useful alongside blood gas analysis, serum electrolytes, and kidney function tests.