How the Anion Gap Reflects
The anion gap is a calculated value from a basic electrolyte panel that helps evaluate blood test interpretation in possible acid-base problems. It represents the relationship between key measured ions, especially serum sodium, serum chloride, and serum bicarbonate. In plain language, the anion gap estimates the amount of unmeasured ions in the blood and can serve as a helpful diagnostic marker for certain metabolic problems.
Because the body works to maintain electroneutrality, the overall positive and negative charges in blood should remain balanced. When measured ions shift, the anion difference can suggest an underlying acid-base disorder. A change in the gap often indicates a metabolic derangement such as metabolic acidosis, where acids increase or bicarbonate is reduced.
The concept is especially helpful in serum chemistry because it gives clinicians a rapid clue about whether the patient may have a high anion gap, a normal anion gap, or a low anion gap. That clue can reduce the list of possible causes and direct further testing.
How an Anion Gap Calculator Works
An anion gap calculator relies on a basic calculation formula built on common laboratory values. Most calculators ask for serum sodium, serum chloride, and serum bicarbonate. Certain versions also allow potassium, which produces a potassium value-based adjustment to the result.
The calculator runs an adjusted calculation that mirrors the basic chemistry of the blood. Sodium is the dominant measured cation, while chloride and bicarbonate are principal measured anions. The remaining difference helps estimate unmeasured ions. This can be valuable in blood test interpretation because the result may reveal a hidden acid load, a change in bicarbonate level, or an abnormal change in the sodium chloride balance.
In practice, the calculator is a quick way for understanding whether there is a gap in the measured ions that could indicate a specific problem. It does not replace a full clinical review, but it can be a practical first step in checking acid-base balance.
Anion Gap Formula Using and Omitting Potassium
There exist two common ways to work out the gap: a traditional formula and a potassium-added formula. The traditional formula usually uses sodium, chloride, and bicarbonate. The potassium-based version adds serum potassium to the cation side of the equation.
A standard traditional formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
A potassium-inclusive formula is:
Anion gap = (serum sodium + serum potassium) - (serum chloride + serum bicarbonate)
Both approaches can be valid, but they do not produce the same number. This potassium-inclusive method usually gives a slightly higher value because potassium is added to the cation total. For that reason, the normal range depends on which formula is used and on the laboratory reference range reported by the lab.
Most clinicians focus on whether the result falls within the expected reference interval for that specific method. A calculator should clearly identify whether it is using the traditional or potassium-inclusive approach, since misreading the formula can lead to confusion in clinical interpretation.
How to Enter Blood Test Values Properly
Precise results hinge on entering the right numbers for blood sodium, chloride, bicarbonate, and when applicable blood potassium. These measurements should come from the same specimen and same time period whenever possible, since mixed timing can alter the result.
Below are the key points to review:
- Enter the reported serum sodium value exactly as listed. Enter serum chloride from the same panel, not a made-up value. Use the measured serum bicarbonate or total CO2 if that is what the lab shows. If the calculator includes blood potassium, input the serum potassium value from the same blood sample. Verify units carefully so the inputs align with the calculator’s expected format.
Small input errors can create a inaccurate low gap result or hide a true high anion gap. If the numbers seem inconsistent with the patient’s condition, verify the laboratory values before drawing conclusions.
Interpreting a High Anion Gap
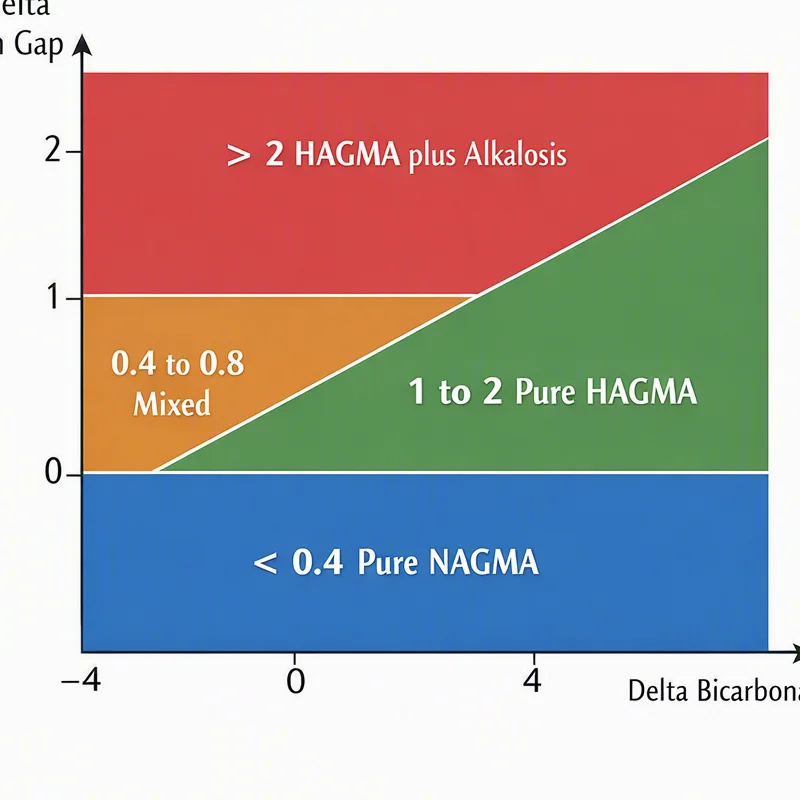
A high anion gap often indicates surplus acids are found in the circulation. This is a typical pattern in metabolic acidemia and is frequently called elevated gap acidosis. The key causes include lactic acidosis, ketone-related acidosis, kidney failure, and toxic alcohol exposure or other toxic ingestion.
In lactic acid buildup, lactate rises because of poor oxygen delivery, shock, severe infection, or impaired metabolism. In ketotic acidosis, ketones rise due to insulin deficiency, starvation, or alcohol-related metabolic states. Renal insufficiency can impair acid excretion and let unmeasured acids to build up. Poisonous alcohols such as methanol or ethylene glycol can also produce a significant gap because their metabolites are acidic.
When the gap is high, the central question is not only what the number is, but what it means in the overall clinical setting. Symptoms, medication history, kidney function, glucose, lactate, ketones, and toxicology may all matter. The anion gap is a clue, not the final diagnosis.
Reading a Standard or Low Anion Gap
A normal anion gap does not exclude acid-base disease. It may simply mean the body’s tested electrolytes are balanced within the normal range. Certain types of metabolic acidosis, especially those with a rise in chloride, may present with a normal gap rather than a high one.
A low anion gap is uncommon and deserves careful review. One major cause is hypoalbuminemia, because albumin is a negatively charged protein that makes up part of the unmeasured anion pool. When albumin is low, the gap can drop even if there is no major acid-base problem.
Other explanations include lab error, hyperchloremia, and paraproteinemia. Hyperchloremia can reduce the gap because chloride rises relative to sodium and bicarbonate. Paraproteinemia, such as that seen in some plasma cell disorders, may also alter the expected balance of ions. Because of this, a low value should be compared against the full serum chemistry panel and repeated if needed.
In many cases, the most useful next step is to look for a measurement issue, verify albumin, and evaluate whether the result matches the patient’s anion gap in chronic kidney disease condition. A low gap can be real, but it can also be a clue that the sample or calculation needs review.
When Potassium Changes the Result
Including serum potassium in the formula can change the final number, but the size of the change is often small. The reason some calculators provide a potassium-inclusive formula is tied to electroneutrality: potassium is a true cation and adds to the total positive charge in the blood.
In routine practice, potassium may slightly elevate the calculated gap, yet the clinical significance depends on how the result is being used. If the potassium value is normal, the difference between the standard and potassium-inclusive methods may not affect management. If potassium is markedly abnormal, the adjusted anion gap can give a more https://anion-gap-formula041.cloudhinter.com/posts/anion-gap-calculator-for-interpreting-serum-chemistry-panels complete picture of the electrolyte state.
That said, most clinicians still rely on the traditional approach because it is widely used in labs and textbooks. The potassium-inclusive method can be especially useful when a calculator is designed to reflect the full measured cation load and when you want a more detailed view of the patient’s electrolytes.
The practical point is this: potassium matters, but whether it changes the interpretation depends on the scenario. A calculator that accepts potassium can be a better option for detailed review, while still requiring sound clinical interpretation.
Limitations of Web-based Anion Gap Calculators
Online calculators are handy, but they have important restrictions. Initially, they use fixed reference limits that may not match every lab’s lab reference range. Different devices, cohorts, and formulas can produce different expected values. A number that looks abnormal in one setting may be acceptable in another.
Next, many calculators do not adjust for albumin correction. Because low albumin can lower the anion gap, uncorrected results may underestimate the presence of an acid load. A proper review may require considering albumin as well as the measured electrolytes.
Also, blood gas and chemistry results are not interchangeable. A venous blood gas may help assess pH and bicarbonate, but its values are not identical to a standard chemistry panel. That difference matters when evaluating metabolic acidosis or a suspected acid-base disorder.
Last, calculators cannot replace clinical context. A result must be interpreted alongside symptoms, medications, kidney function, glucose, ketones, lactate, and other lab findings. The calculator is a tool for pattern recognition, not a standalone diagnosis.
FAQ
What is an anion gap calculator used for?
An anion gap calculator is used for blood test interpretation when reviewing a serum chemistry panel. It helps estimate whether there is a hidden acid load, making it useful for detecting metabolic acidosis, especially high anion gap states. It can also help identify a normal anion gap or low anion gap that may need further review.
Should potassium be included in the anion gap formula?
Potassium is included in some formulas, especially the potassium-inclusive formula, but not all calculators use it. The traditional formula is more common, while the potassium version may better reflect total measured cations in certain cases. Whether to include potassium depends on the calculator design, lab method, and the purpose of the clinical interpretation.
What is a normal anion gap range?
The normal range depends on the equation and the laboratory. Some labs use a separate lab reference range for the traditional formula than for the potassium-based method. Because of this, the most reliable approach is to compare the result with the specific normal interval reported by the laboratory rather than relying on one universal number.
What can a high anion gap mean?
A raised anion gap usually suggests metabolic acidosis from unmeasured acids. Common causes include lactate buildup, ketotic acidosis, kidney failure, and toxic alcohol exposure or other forms of toxic ingestion. It is a clue that should be assessed with the rest of the electrolyte panel and the patient’s medical context.
Can a low anion gap be caused by lab error or low albumin?
Yes. A low anion gap can be caused by testing error or from hypoalbuminemia, since the albumin level is a major unmeasured anion. Other causes include elevated chloride and paraproteinemia. If the result is unexpected, it is reasonable to verify the sodium level, potassium level, serum chloride, and blood bicarbonate values and review the full laboratory picture.