Defining starvation ketoacidosis?
Starvation ketoacidosis is one type of metabolic acidosis that appears when the body does not receive enough carbohydrate intake or total calories and begins relying heavily on fat for fuel. This shift leads to ketosis, a state in which the liver generates ketone bodies https://pastelink.net/ugjetfn6 to provide energy. When this process becomes stronger, acid production rises enough to affect acid-base balance and modify laboratory values.
The trigger is usually fasting, prolonged poor intake, or malnutrition. In these settings, the body experiences an energy deficit and a gradual drop in circulating glucose availability. As glucose availability falls, the body increases fat metabolism, which raises ketoacid production. This is different from everyday short-term ketosis because starvation states can produce a clinically meaningful acid-base disturbance.
Starvation ketoacidosis often occurs when nutritional deprivation is severe enough that the liver generates more acidic byproducts than the body can easily buffer. The main ketone-related acids are beta-hydroxybutyrate and acetoacetate. These compounds are part of normal ketone physiology, but in excessive amounts they contribute to metabolic derangement and a recognizable pattern of high anion gap metabolic acidosis.
Understanding this process matters because not all ketosis is the same. In starvation ketoacidosis, the key issue is not simply the presence of ketones, but the combination of glucose depletion, acid generation, and the resulting change in laboratory interpretation. That is why the Anion Gap Calculator can be helpful as a quick tool for clinical interpretation of the lab pattern.
Why starvation ketoacidosis Raises the Anion Gap
The anion gap increases when acids build up in the blood and their charged components are not directly measured in a standard electrolyte panel. In starvation ketoacidosis, the major cause is the buildup of unmeasured anions produced from ketone bodies. As beta-hydroxybutyrate and acetoacetate accumulate, they use up buffering capacity and leave behind negatively charged acid metabolites that increase the gap.
This is the classic mechanism of a high-gap acidosis. The body responds to acid buildup by lowering bicarbonate, which is the primary buffer spent during acidosis. As bicarbonate falls, the gap often widens because the lost buffer is functionally replaced by acidic anions that are not directly reflected in routine chemistry values.
The process is driven by ketone accumulation during prolonged fasting or nutritional deprivation. When insulin levels are relatively low and glucose intake is insufficient, the body shifts toward ketone production for fuel. This adaptive response becomes harmful when ketone generation outpaces utilization and elimination. The resulting organic acids disrupt acid-base balance and produce the elevated anion gap seen on labs.
Although both ketone bodies contribute, beta-hydroxybutyrate is often the dominant acid in more significant ketoacid states. Acetoacetate also contributes to the measured acid load, but the total burden depends on severity, duration, and physiologic stress. The important point is that the ketones function as organic acids, and their presence explains why starvation ketoacidosis is a true cause of anion gap calculation abnormalities rather than a benign lab curiosity.
Put simply: starvation produces an energy shortage, the body burns fat, fat metabolism yields ketones, and those ketones act as unmeasured acids. That chain of events is why the anion gap goes up.
How to Work Out and Analyze the Anion Gap
An Anion Gap Calculator can help estimate whether the electrolyte balance supports a high-gap acidosis. The usual calculation is based on sodium, chloride, and bicarbonate:
Anion gap = sodium - (chloride + bicarbonate)
This calculation is easy to use, but the meaning depends on the overall clinical setting. A elevated result may indicate too many unmeasured anions, while a typical result makes starvation ketoacidosis less probable or suggests an initial / milder stage. Because lab reference ranges vary, the exact cutoff should be evaluated with the laboratory-specific values and the patient’s general condition.
In starvation ketoacidosis, the gap goes up because bicarbonate is used up to buffer the acids generated by ketogenesis. The low bicarbonate often tracks the severity of acidosis. Meanwhile, chloride may appear relatively normal or may go up in mixed patterns depending on volume status and replacement fluids. Sodium is necessary for the calculation and may also change with dehydration, poor intake, or concurrent illness.
When working with an Anion Gap Calculator, it can help to think in terms of clinical interpretation rather than a single result. A somewhat elevated gap may still be significant if the patient has clear starvation, vomiting, poor oral intake, or visible ketosis. A markedly high value suggests a more intense metabolic acidosis or another additional cause of high anion gap metabolic acidosis.
To interpret the result accurately, review the gap with the rest of the laboratory picture:
- Sodium: helps anchor the overall calculation and judge hydration or dilutional effects. Chloride: helps clarify whether the acidosis is accompanied by compensatory or mixed changes. Bicarbonate: often falls as acid load increases and is a key marker of disease intensity.
The calculation is merely an element of the whole picture. The goal is not merely to detect an out-of-range result, but to relate it to the overall pattern of ketotic state, acid-base disturbance, and the probable cause of the metabolic derangement.
Characteristic Laboratory Findings in Starvation Ketoacidosis
Starvation ketoacidosis has a recognizable laboratory pattern, although the exact pattern varies depending on the length of fasting, degree of malnutrition, and any associated illness. The most helpful tests often include serum glucose, electrolytes, arterial blood gas, and serum ketones.
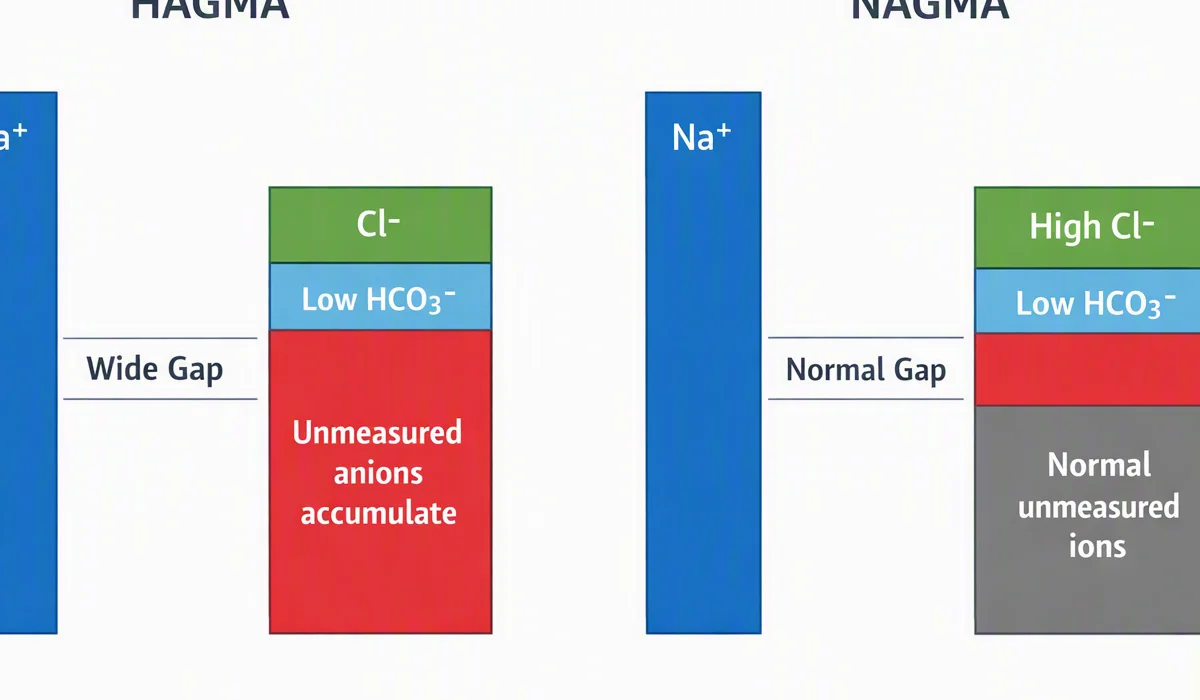
Serum glucose is often not elevated or low rather than markedly elevated. One of the main clues separating starvation ketoacidosis from other forms of ketoacidosis. Because the underlying problem is lack of intake rather than excess glucose, the glucose level may reflect exhaustion rather than hyperglycemia.
Electrolytes often show the biochemical signature of acid-base stress. The bicarbonate level is usually low, supporting the diagnosis of metabolic acidosis. Sodium and chloride may vary depending on fluid losses, vomiting, dehydration, or treatment before testing. Assessing the entire set of serum electrolytes helps determine whether the picture is isolated or mixed.
Serum ketones are typically positive, and if quantitative testing is available, elevated beta-hydroxybutyrate supports the diagnosis more strongly than a basic urine ketone screen alone. This is because urine ketone testing may underrepresent the burden of beta-hydroxybutyrate. In starvation states, beta-hydroxybutyrate can be disproportionately elevated and is a major driver of the acid load.
An arterial blood gas may show acidemia with a low bicarbonate and compensatory respiratory changes. A patient may develop compensatory hyperventilation as the body tries to lower carbon dioxide and offset the acid load. This respiratory response helps maintain pH, but it does not correct the underlying problem.
Findings often include:
- Low or normal serum glucose Low bicarbonate Positive serum ketones Elevated beta-hydroxybutyrate and acetoacetate Abnormal electrolytes Acid-base changes on arterial blood gas
These findings support the diagnosis, but they also help estimate severity. The more pronounced the acidosis and ketone burden, the more likely the anion gap is to be clearly elevated.
How It Varies From Diabetic Ketoacidosis and Other Causes
Starvation ketoacidosis can look similar to other forms of high anion gap metabolic acidosis, so separating it from related conditions is crucial. Its closest mimic is diabetic ketoacidosis, but there are several key differences.
In diabetic ketoacidosis, the core issue is insulin deficiency, which promotes severe ketone production and usually produces far higher glucose levels. Starvation ketoacidosis, by contrast, is driven by glucose depletion and inadequate intake. The patient may have normal or low glucose rather than marked hyperglycemia. That distinction changes both the diagnostic thinking and treatment priorities.
Alcoholic ketoacidosis is another notable differential. It often occurs after poor intake combined with heavy alcohol use and may share features of starvation physiology. Like starvation ketoacidosis, it can produce ketone-related acids and an elevated anion gap. The broader context, however, differs, and alcohol use can add extra metabolic complexity.
Lactic acidosis is another major cause of high anion gap metabolic acidosis. Instead of ketone bodies, lactate is the main unmeasured anion. Lactic acidosis may occur with tissue hypoperfusion, sepsis, or other forms of metabolic stress. If lactate is elevated, it can explain part or all of the gap, even if ketosis is present at the same time.
Renal failure can also raise the gap because failing kidneys cannot remove acids efficiently. In that setting, retained acids and other retained solutes contribute to the anion gap. Renal impairment can coexist with starvation or dehydration, which makes interpretation more challenging and reinforces the need for deliberate diagnostic evaluation.
The key differences often come down to the pattern of labs and the clinical story:
- Diabetic ketoacidosis: usually marked hyperglycemia and insulin deficiency Starvation ketoacidosis: fasting, malnutrition, low or normal glucose, ketone-driven acidosis Alcoholic ketoacidosis: alcohol use plus poor intake, overlapping metabolic features Lactic acidosis: elevated lactate from hypoperfusion or stress Renal failure: impaired acid clearance and retained metabolic acids
Because these conditions can overlap, the best approach is to use the anion gap as a first step, not the final diagnosis. The gap identifies the presence of excess unmeasured anions, but only the rest of the clinical picture can determine the cause.

When a High Anion Gap Needs Prompt Evaluation
A elevated anion gap consistently requires evaluation, but the urgency depends on the severity, related symptoms, and the general acid-base disorder. Starvation ketoacidosis may be mild in some cases, but it can still become dangerous if the patient is dehydrated, unable to eat, or has another illness contributing to the metabolic disturbance.
Immediate evaluation is necessary when symptoms suggest worsening acidosis or systemic illness. These may include mental status changes, significant weakness, persistent vomiting, increased respiratory rate, dehydration, or inability to maintain intake. A patient with clear acidemia on an arterial blood gas and an increased gap needs prompt clinical assessment rather than simple observation.
The concern is not only the ketones themselves, but the overall acid-base balance. If bicarbonate continues to drop, the acidosis can worsen. If the patient has concurrent infection, vomiting, renal impairment, or significant volume depletion, the metabolic picture can worsen quickly.
Helpful considerations during assessment include:
- The duration for which the patient has had reduced intake or fasting Whether there is malnutrition or ongoing lack of adequate nutrition Evidence of ketosis or substantial ketone burden Whether serum glucose is decreased, normal, or high Whether another cause of high anion gap metabolic acidosis may also be present
If the patient is symptomatic or the laboratory values show a significant metabolic derangement, the issue should be treated as beyond a simple electrolyte abnormality. The elevation in the anion gap is a marker of underlying acid production, and the reason for that acid load must be identified.
Frequently Asked Questions About Starvation Ketoacidosis and Anion Gap
Does fasting ketoacidosis always cause a elevated anion gap?
Not in every case, but it often does. Starvation ketoacidosis typically increases the anion gap because ketone-related acids produce unmeasured anions. In mild or subtle cases, the gap may be only slightly elevated or even appear almost normal if the acid load is small or if other electrolyte changes are present. The overall clinical context and anion gap interpretation count as much as the number itself.
How large is the anion gap in starvation ketoacidosis?
The amount of elevation differs with the severity of ketosis, duration of fasting, and presence of other illnesses. Some cases show a slight to moderate rise, while more severe starvation ketoacidosis can produce clear high anion gap metabolic acidosis. The exact level is secondary than whether the result aligns with the rest of the picture, including bicarbonate, serum glucose, and ketone testing.
What lab tests help confirm fasting ketoacidosis?
The most useful tests include serum glucose, electrolytes, arterial blood gas, and serum ketones. Quantitative beta-hydroxybutyrate is especially helpful because it reflects the main ketone burden more precisely than some urine tests. These results, combined with the history of low food intake or malnutrition, support the diagnosis.
How is fasting ketoacidosis different from DKA?
Diabetic ketoacidosis is driven by insulin deficiency and usually presents with markedly elevated glucose levels. Fasting ketoacidosis is caused by glucose depletion from inadequate intake and often has low or low serum glucose. Both can produce ketosis and elevated anion gap acidosis, but the trigger, lab pattern, and treatment approach differ.
Can the anion gap return to baseline after therapy?
Certainly. Once the underlying cause is treated, ketone production decreases, unmeasured anions lessen, and the anion gap can return toward typical values. Treatment usually targets the energy deficit, fluid balance, and electrolyte disturbances, which helps reestablish acid-base balance. Follow-up laboratory values are often used to show improvement in metabolic acidosis and overall metabolism.
Starvation ketoacidosis is a real acid-base problem, not just a benign ketotic state. The key pattern is the increase in the anion gap from ketone-related organic acids, especially beta-hydroxybutyrate and acetoacetate, during periods of fasting or malnutrition. An Anion Gap Calculator helps you identify that pattern rapidly, but the most accurate interpretation always comes from combining the calculation with the clinical story, laboratory values, and thorough medical assessment.