What Are the Anion Gap and Why It Matters
The anion-gap value is a derived value that helps clinicians assess acid base balance by contrasting common blood electrolytes measured on routine blood testing. It is especially helpful when reviewing alkalosis or other forms of acid-base disturbance because it can reveal whether there are hidden acids or other shifts that are not obvious from the basic lab numbers alone.
In practical terms, the anion gap helps understand the relationship between positively charged ions and negatively charged ions in the bloodstream. Most often, the main measured values are sodium, chloride, and bicarbonate, while other contributors such as albumin and hidden anions may affect the result. That is why the anion gap is more than a number; it is a clue that guides medical interpretation of a patient’s status.
Although the anion gap is commonly discussed in metabolic acidosis, it also matters in metabolic alkalosis because the surrounding clinical context can change how the result is read. A normal, corrected, or elevated value may suggest different underlying processes, especially when paired with other blood electrolytes and lab values from a chemistry panel.
In what way an Anion Gap Calculator Operates
An anion gap calculator is a medical calculator that automates the anion gap formula so you can easily review blood test results. The typical calculation formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This equation uses serum sodium, serum chloride, and serum bicarbonate because they are the main values available on a standard electrolyte panel. Sodium is the primary measured cation, while chloride and bicarbonate are the principal measured anions used in the calculation. The result is then compared with a reference interval or reference range to determine whether the value is expected or unexpected.
Many calculators also offer an optional albumin adjustment. Since albumin is a important unmeasured anion, a low albumin level can make the anion gap appear seemingly normal. A well-designed calculator therefore acts as both a diagnostic tool and an interpretation guide, helping with clinical decision making when the numbers do not align with the expected pattern.
Anion Gap in Metabolic Alkalosis: Interpretation Basics
In alkalotic metabolic state, the body has a primary increase in bicarbonate or acid loss, and the anion gap may seem unchanged, slightly changed, or elevated depending on the cause and the patient’s compensatory state. Understanding the anion gap in this setting requires more than simply reading the number; it requires attention to physiologic compensation and the full pattern of lab findings.
A standard anion gap in metabolic alkalosis often suggests that the alkalosis is due to chloride loss, volume changes, or other processes that do not add excess acids to the bloodstream. An elevated result may suggest a dual disturbance, such as concurrent metabolic acidosis, or hidden contributions from unmeasured acids. This is where albumin becomes important, because low albumin can mask a truly increased gap.
For that reason, many clinicians rely on the adjusted anion gap rather than the unadjusted value. The corrected value gives a more accurate picture of lab interpretation, especially when metabolic alkalosis coexists with other changes in acid-base equilibrium. In short, the calculator does not replace judgment; it improves the quality of that judgment.
Inputs Needed for the Calculator
A dependable calculator usually requires four inputs: serum sodium, serum chloride, serum bicarbonate, and serum albumin. These measurements are taken from a standard blood chemistry panel or electrolyte panel, and each helps refine the final interpretation.
- Serum sodium: the main cation used in the formula. Serum chloride: a significant measured anion that helps determine the gap. Serum bicarbonate: reflects buffering status and is central to acid-base assessment. Serum albumin: used in albumin correction when required.
These measurements also support wider lab result analysis. For example, a low bicarbonate may suggest metabolic acidosis, while an elevated bicarbonate fits better with metabolic alkalosis. Chloride trends can help identify chloride-responsive patterns, and albumin helps prevent underestimating the anion gap in patients with hypoalbuminemia.
When any of these values are missing, interpretation becomes less precise. The calculator may still generate a number, but without the full dataset, the result may not reflect the true clinical context.
Step by Step Calculation Illustration
Here is a basic sample calculation with typical lab values:
- Serum sodium: 140 Chloride level: 100 Bicarbonate level: 30
With the equation:
Anion gap = 140 - (100 + 30) = 10
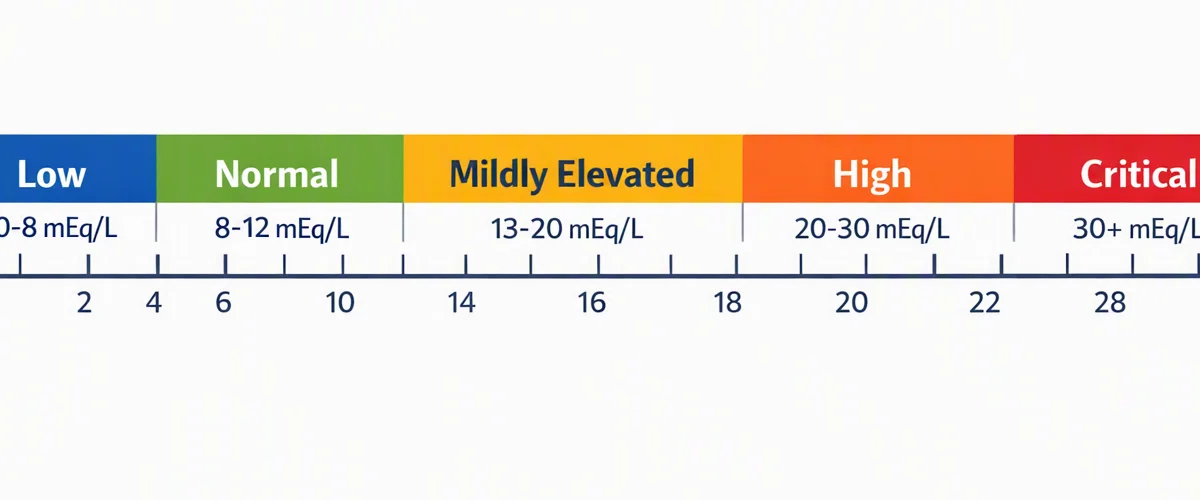
Provided that the usual reference range is roughly 8 to 12, this result would be considered as a normal anion gap. In a patient with metabolic alkalosis, that may point to a chloride-associated or volume-associated cause rather than a hidden acid load.
Next, consider a second example:
- Na: 140 Serum chloride: 94 Serum bicarbonate: 30
Anion gap = 140 - (94 + 30) = 16
This value may fall into an increased anion gap pattern depending on the lab’s normal interval. With metabolic alkalosis present, that increases the possibility of a complex acid-base disorder or another process such as lactate buildup that is altering the overall interpretation.
Causes of alkalosis with Typical or Increased Anion Gap
Several conditions can result in alkalosis while the anion gap is left unchanged or turns unexpectedly elevated. The main real-world triggers include vomiting, diuretic use, and volume depletion. These can lower chloride, affect renal handling of bicarbonate, and create a pattern that suggests alkalosis even when another issue is present.
Vomiting can result in loss of gastric acid, which increases bicarbonate relative to chloride. Diuretic use often drives sodium and chloride loss, leading to contraction alkalosis and a typical electrolyte pattern. Volume depletion can further intensify renal bicarbonate retention and generate a strong compensatory response.
An elevated gap in a patient who looks alkalotic should require careful review for overlapping disorders. One important example is lactic acidosis, which can coexist with alkalosis and raise the combined gap. This is why the calculator should always be used as part of a wider clinical interpretation rather than as a standalone answer.
How to Calculate the Anion Gap for Albumin
Albumin correction is essential because albumin is a negative protein that contributes significantly to the unmeasured anion pool. When albumin is low, the measured anion gap may look misleadingly normal. This is especially relevant in patients with hypoalbuminemia, where the uncorrected number can underestimate the true acid burden.
Many clinicians use a corrected anion gap to improve test interpretation. A common approach is to include a fixed value for each gram per deciliter that albumin falls below normal, though the exact correction used can change by institution. The key point is that a corrected anion gap gives a more precise picture of the patient’s acid-base status.
For example, a patient with a borderline-normal value may actually have an elevated corrected result after adjustment for albumin. That corrected value can change the overall reading from simple metabolic alkalosis to a mixed acid-base imbalance. This is why albumin should be reviewed in addition to serum sodium, serum chloride, and serum bicarbonate whenever possible.
When an Anion Gap Calculator Is Most Useful
An anion gap calculator is particularly helpful when a clinician needs fast, structured clinical decision support from a blood chemistry panel. It is most helpful when the lab pattern is initially confusing or when multiple processes may be occurring at the same time.
Common situations include:
- Assessing an electrolyte panel in a patient with unclear bicarbonate changes Searching for hidden acid-base disorders in apparent metabolic alkalosis Reviewing serial laboratory values during treatment Evaluating whether a corrected anion gap changes the interpretation Aiding diagnosis when symptoms and labs do not match neatly
The tool is also useful for documentation and communication. When the calculation is done in a consistent way, it provides a clear structure for discussing acid-base patterns with other clinicians. That consistency improves clinical interpretation and helps avoid overlooking a mixed disorder.
Limitations and Common Calculation Errors
Even a well-designed calculator has restrictions. Lab variability between instruments or facilities can alter the result slightly, and measurement error can affect sodium, chloride, or bicarbonate values enough to change the final gap. Because the formula depends on small differences between numbers, even modest inconsistencies can make a difference.
Another major limitation is that the anion gap only estimates a portion of the body’s charged particles. It does not directly measure all acids or bases, and unmeasured anions may be present even when anion gap and toxic alcohols the value seems normal. That is why the result must always be considered in clinical context, not in isolation.
Common calculation errors include entering the wrong units, using outdated values, or forgetting to apply albumin correction when indicated. Misreading the reference range is another recurring problem because different laboratories may use different reference intervals. A result that is normal in one setting may be marginal in another.
Finally, note that an anion gap is not a replacement for a full acid-base evaluation. It is one part of the bigger picture that includes signs, prescriptions, volume status, and the broader pattern of serum electrolytes. If used well, it enhances lab result analysis; if used by itself, it can give a false impression.
FAQ About Anion Gap and Metabolic Alkalosis
How is an anion gap calculator used for?
An anion gap calculator is used to rapidly calculate the anion gap from serum sodium, serum chloride, and serum bicarbonate. It helps with clinical interpretation of acid-base balance, reveals possible electrolyte imbalance, and helps with evaluation of metabolic alkalosis or metabolic acidosis. When albumin is included, it can also deliver a corrected anion gap for better laboratory interpretation.
Can metabolic alkalosis affect the anion gap?
Yes. Metabolic alkalosis can be associated with a normal anion gap, and in some cases it may occur alongside an elevated anion gap if another disorder is present. The final reading depends on the overall situation, albumin level, volume status, and whether there are unmeasured anions contributing to the result. For this reason the anion gap calculator should be used as within a broader acid-base disorder assessment.
How do you calculate the anion gap from lab values?
The most common anion gap formula is serum sodium minus the sum of serum chloride and serum bicarbonate. That is, sodium - (chloride + bicarbonate). This calculation uses values from an electrolyte panel or blood chemistry panel and is then compared with the reference range to determine whether the result is within range or elevated.
Why should albumin be used to correct the anion gap?
Albumin should be used because it is a key unmeasured anion. When albumin is low, especially in hypoalbuminemia, the uncorrected anion gap may look artificially normal. Albumin correction helps reveal the corrected anion gap, which provides improved clinical interpretation and more reliable lab result analysis.
What does a normal or high anion gap indicate in alkalosis?
A typical anion gap in metabolic alkalosis often suggests chloride loss, vomiting, diuretic use, or volume depletion. A raised anion gap can mean that another process may also be present, such as lactic acidosis or another acid-base disorder. The key is to interpret the value with the patient’s clinical context, albumin level, and full blood test results rather than using the number alone.