What an Anion Gap Shows
The anion gap is a estimated value used in clinical laboratory practice to estimate the difference between routinely measured cations and anions in electrolytes. In clinical practice, it helps physicians and laboratory staff think about the distribution of charged particles in blood and whether there are extra unmeasured anions present. This makes it a valuable marker of electrolyte balance and broader acid-base status.
An Anion Gap Calculator is a fast diagnostic aid that turns common lab values into an interpretable number. The result does not diagnose a disorder by itself, but it provides important context to a patient’s serum chemistry and overall electrochemical balance. Because the anion gap reflects the relationship between positive and negative ions, it can reveal an underlying metabolic disturbance even when the rest of the panel seems only mildly abnormal.
From a physiology perspective, the anion gap is a window into buffer systems and acid accumulation. When acids accumulate, their anions may not be directly measured in a standard electrolyte panel. That is why the anion gap acts as a kind of anion difference—a practical measure that can point toward hidden biochemical changes.
In lab practice, the value is best understood as part of a broader clinical interpretation. It complements, rather than replaces, history, exam findings, and other tests. Used correctly, it can help narrow a differential diagnosis and guide follow-up testing.
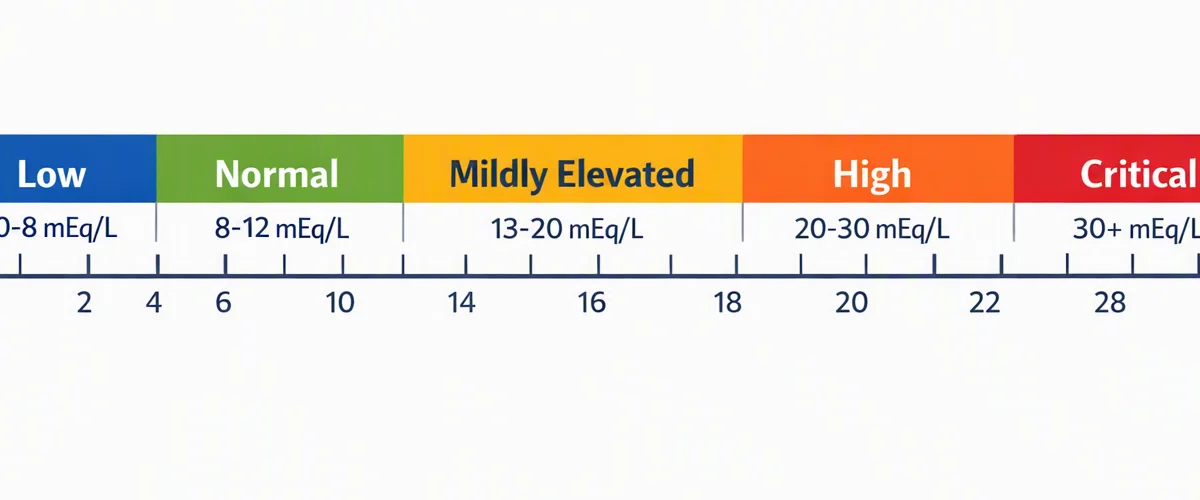
Formula and Calculation of the Anion Gap & Calculation Inputs
The core computational formula is straightforward. Most commonly, the anion gap is calculated from sodium, chloride, and bicarbonate:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain laboratories report a slightly different version if potassium is included, but the sodium-based formula is the most widely used in routine practice. An Anion Gap Calculator directly applies this formula and returns a result that can be compared with the local interpretive range.
These inputs come from the serum chemistry or chemistry analyzer output:
- Sodium: the major measured extracellular cation. Chloride: the main measured anion. Bicarbonate: commonly listed as total CO2 on the chemistry panel, acting as a bicarbonate substitute in many settings.
Because the result depends entirely on these three values, the quality of the output depends on the quality of the input. A small error in any one test can shift the final number enough to change clinical interpretation. This is why understanding the underlying measurement method is significant in laboratory medicine.
Many people think of the result as a single number, but it is more helpful to view it as a reflection of the underlying serum chemistry and the patient’s current acid-base status. When the calculator output is unexpected, it is worth reviewing the original analytes before drawing conclusions.
How to Read a Normal, Raised, or Low Anion Gap
Assessment relies on the local reference range. Multiple laboratories may use different analyzers, calibration approaches, and reporting conventions, so there is no universal “normal” value that applies everywhere. The same numeric result may be interpreted another way depending on the platform and the institution’s reference range.
A normal anion gap suggests that the measured electrolytes are in expected proportion and that there is no clear increase in unmeasured anions. However, a normal value does not eliminate disease. Some forms of metabolic acidosis occur with a normal anion gap, especially when bicarbonate loss is matched by chloride gain.
A high anion gap suggests that more acids or negatively charged substances are present in the blood. This pattern is classically associated with high anion gap metabolic acidosis, where the extra acid is reflected in the increased gap. In contrast, a normal value in the setting of acidosis can point toward normal anion gap metabolic acidosis, which has a different set of etiologies and follow-up steps.
Albumin is one of the key modifiers of interpretation. Because albumin is a negatively charged protein, lower levels can reduce the apparent gap and mask clinically important acid-base changes. That means interpretation should always consider whether the measured number fits the patient’s broader biochemical picture.
In practice, the result is best interpreted as part of the complete acid-base disorders assessment, not as a stand-alone answer. The same number can mean different things depending on whether the patient has symptoms, abnormal lactate, renal dysfunction, or other lab abnormalities.
Albumin Adjustment and Its Clinical Significance
Hypoalbuminemia is a common reason the measured anion gap can underestimate the true amount of hidden acids. Since serum albumin carries a negative charge, a reduced albumin concentration diminishes the expected gap even when other acids are present. This is why many laboratory clinicians use a corrected anion gap.
The corrected result modifies the observed value upward when albumin is low, making the estimate more medically relevant. In many workflows, albumin correction helps uncover a hidden metabolic acidosis that might otherwise appear minimal or even absent. The goal is not to force every result into a single interpretation, but to improve the accuracy of the corrected result when protein abnormalities are present.
Why it matters:
- It improves detection of acid-base abnormalities when serum albumin is low. It helps prevent underestimating high anion gap metabolic acidosis. It aids better clinical interpretation in very ill or hospitalized patients.
A calculator that includes albumin correction can be especially helpful because it transforms a raw number into a more meaningful estimate of acid-base burden. In other words, the adjusted value can better reflect the patient’s actual electrolyte balance and the likely presence of unmeasured anions.
For laboratory medicine, the key point is that a single uncorrected number may be incomplete. When albumin is low, the Anion Gap Calculator should be used as a screening tool plus a first step for further assessment rather than the final word.
Frequent Causes of an Elevated Anion Gap
An elevated result often points delta ratio calculator free to acid accumulation from additional organic or inorganic acids. The classic principle is high anion gap metabolic acidosis, but test interpretation should emphasize the root cause rather than the pattern alone.
Three of the most common causes are lactic acidosis, ketoacidosis, and renal failure.
- Lactic acidosis: Increased lactate production or impaired clearance can elevate the gap as lactate-associated anions accumulate. Ketoacidosis: Ketone bodies contribute unmeasured anions, often resulting in a clearly elevated gap. Renal failure: Reduced excretion of acid byproducts can lead to retention of unmeasured anions and a increasing gap.
Other causes may also be present, but these three diagnoses are common anchor points in the differential diagnosis. In the laboratory context, the anion gap helps decide whether a patient’s metabolic disturbance is likely due to hidden acid retention or to another mechanism.
It is helpful to remember that an elevated gap is not itself a diagnosis. Instead, it is a clue that prompts additional testing, such as lactate, ketones, renal function markers, or toxicology studies when appropriate. The value becomes most useful when paired with other lab values and the clinical picture.
Reasons of a Decreased Anion Gap
A reduced result is rarer than a raised one, but it can still be diagnostically important. The leading explanation is hypoalbuminemia, because a decreased albumin level depresses the expected number. If albumin is not considered, the result may look deceptively unremarkable or simply “off” without a clear reason.
Paraproteinemia is another significant cause. Certain abnormal proteins can alter the charge balance in blood and lower the measured gap. In some patients, this finding may be an early clue that further evaluation of protein abnormalities is needed.
Laboratory error must also be considered. A low value may reflect a specimen issue, analyzer issue, or transcription problem rather than true physiology. That is why repeating the panel and reviewing the original serum chemistry is often the first practical step.
Other reasons can include interference with the measurement method or unusual shifts in electrolytes, but the three major causes above should be checked first. When the result is unexpectedly low, the best practice is to verify the numbers, review the patient’s albumin, and reassess whether the result fits the broader biochemical context.
Although clinicians often focus on elevated values, a low gap can reveal meaningful disease or analytical issues. In laboratory medicine, that makes it just as important to the overall interpretation process.
Practical Applications in Laboratory Medicine
The anion gap has a clear role in evaluating acid-base disorders. In everyday laboratory medicine, it is frequently used alongside the arterial blood gas and the serum chemistry panel to aid in identifying whether a patient has an acid-base problem and what form it may be.
These uses often include:
- Detecting a possible hidden metabolic problem when bicarbonate is low. Assisting in classifying metabolic acidosis as high gap or normal gap. Aiding the evaluation of unexplained electrolyte abnormalities. Offering a quick screening tool before more specialized testing.
In a workflow setting, the calculator can link serum chemistry results with the broader acid-base picture. For instance, a low bicarbonate on the chemistry panel plus an increased gap suggests acid retention rather than simple bicarbonate loss. That distinction is important because it changes the next diagnostic step.
The result also assists with clinical interpretation when the arterial blood gas and chemistry panel do not seem to match perfectly. This can happen because of timing differences, sample handling, or different measurement platforms. The anion gap ties together those data points and provides a practical way to interpret the patient’s acid-base status.
In practice, the calculator is more than arithmetic. It is a structured way to turn routine lab data into a more informative assessment of metabolic health.
Constraints, Pitfalls, and Best Practices
Although the anion gap is helpful, it has important limitations. The main limitation is that the result depends on how the lab measures electrolytes. Current analyzers often anion gap in chronic kidney disease use ion-selective electrodes, and different platforms can yield different numeric results. This means the same patient may have a different reported gap from one system to another.
Measurement error can also distort the answer. Small inaccuracies in sodium, chloride, or bicarbonate can shift the gap enough to change interpretation, especially when the result is near the reference range. Preanalytical issues, sample contamination, and analyzer interference should all be considered when the number seems inconsistent with the clinical picture.
The delta gap is another useful concept in challenging cases. It compares the change in the anion gap with the change in bicarbonate, helping to identify mixed acid-base disorders. In other words, it can show whether several process is affecting the patient at the same time. This is especially valuable when the raw number alone does not explain the overall pattern.
Good practice for using the calculator include:
- Confirm the inputs are from the same sample and the same time point when possible. Consider the local reference range rather than assuming a universal normal value. Review serum albumin before final interpretation. Consider ion-selective electrodes and platform differences when comparing results. Consider using the delta gap when mixed disorders are suspected.
In summary, the anion gap should be interpreted as part of the overall acid-base disorders assessment. It is a strong clue, not a standalone diagnosis. When used with the rest of the electrolyte panel and the clinical context, it becomes a practical tool for laboratory medicine.
FAQ About the Anion Gap Calculator
What is an Anion Gap Calculator used for?
An anion gap calculator is used to rapidly estimate the discrepancy between measured cations and anions from routine lab values. It helps with interpretation of electrolyte data, supports assessment of metabolic acidosis, and can point to the presence of unmeasured anions. In laboratory medicine, it serves as a helpful diagnostic aid rather than a final diagnosis.
How do you calculate the anion gap from lab values?
The usual calculation formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Many calculators use values from a standard electrolyte panel or serum chemistry report. The result should then be compared with the lab’s reference range for accurate interpretation.
When do you need the anion gap be corrected for albumin?
Use albumin correction when serum albumin is low, especially in hypoalbuminemia. Low albumin can make the measured gap look falsely normal or low, so a corrected anion gap can provide a more accurate assessment of the patient’s acid-base state. This is particularly useful when evaluating suspected metabolic acidosis.
What might a high anion gap indicate?
A high value usually suggests high anion gap metabolic acidosis, meaning extra acids or other unmeasured anions are present. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted alongside the rest of the lab data and clinical findings to narrow the differential diagnosis.
May a low anion gap be clinically significant?
Yes. A low result can point to hypoalbuminemia, paraproteinemia, or laboratory error. It may also reflect analytical or preanalytical issues affecting the measurement method. Even if less dramatic than a high value, a low result can still be an meaningful clue in laboratory medicine and should not be ignored.